
Home / V0.5
Turn every training encounter into a lasting lesson.
A scenario ends. Its lessons shouldn’t. Vecco Med’s approach to ambient intelligence starts in medical training—connecting the encounter, the instructor-led debrief and the next opportunity to practice. The ambition is simple: make experience useful beyond a single session, with medics at the center of the learning.
Read the overviewExplore the source
4 formats / one perspectiveInfographic
From encounter to capability
A visual guide to the audience’s training-first story. Open full-size artwork or its written description below.
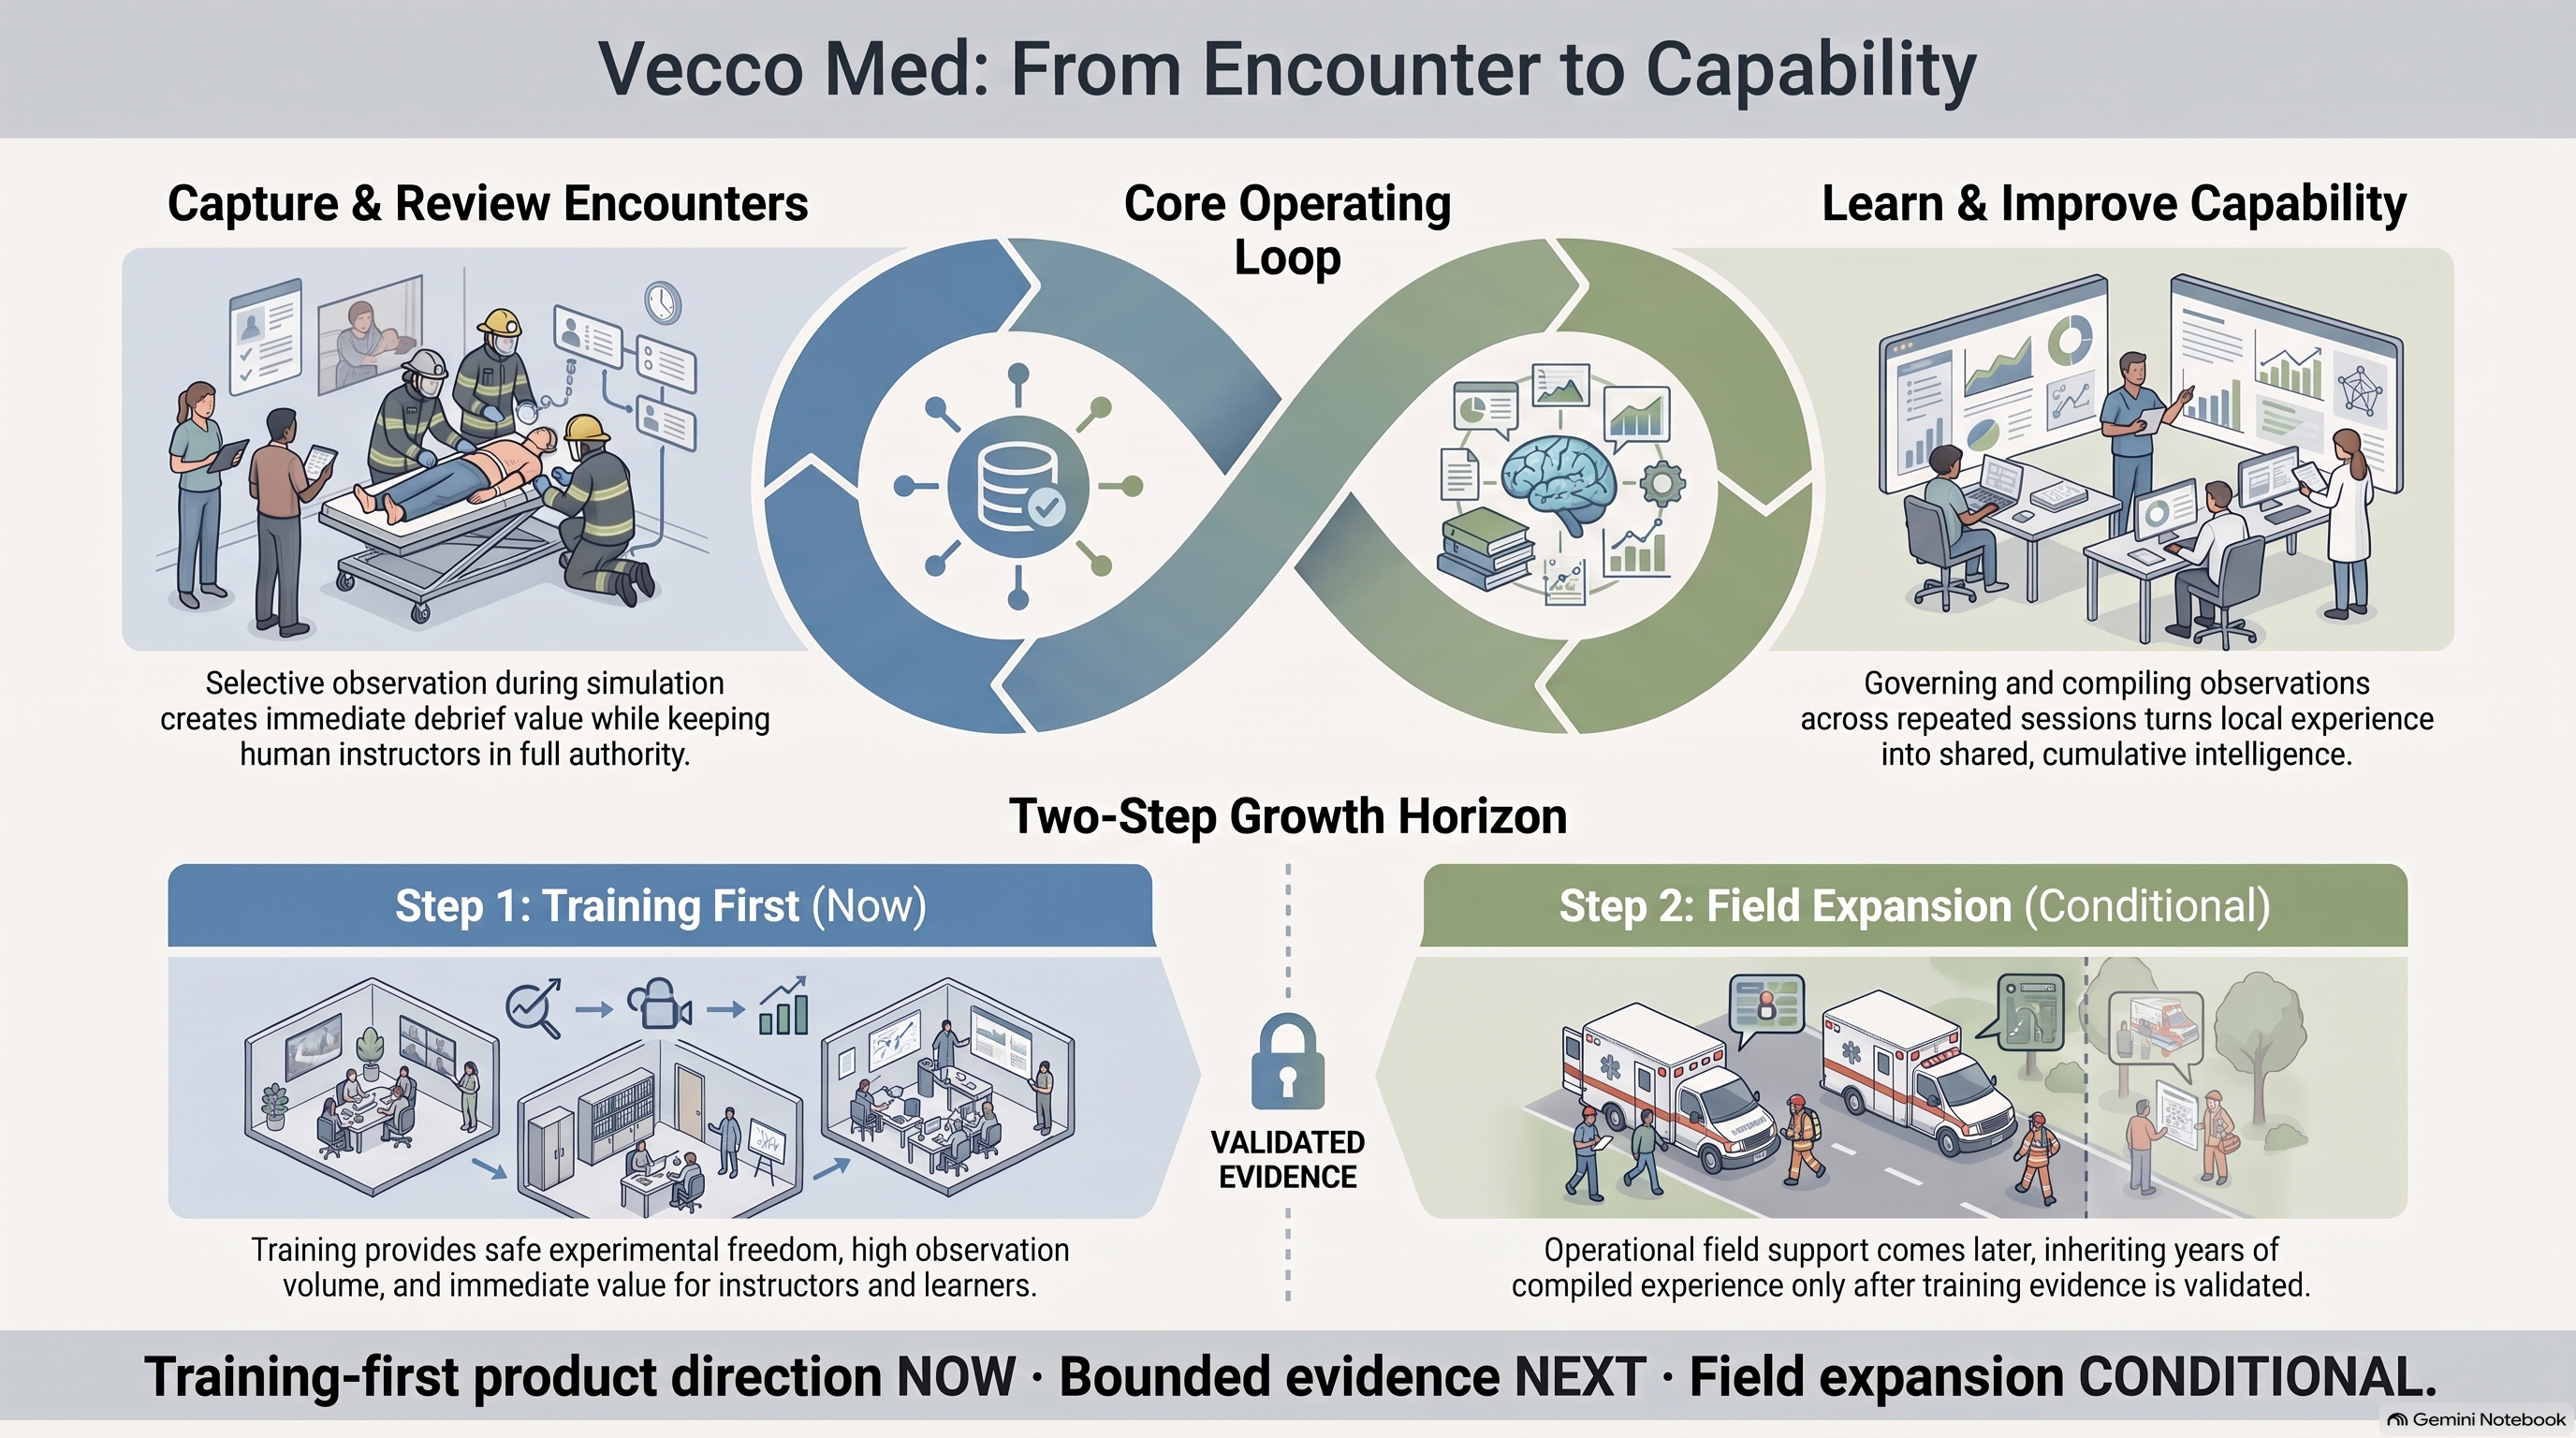 View full size ↗
We couldn’t load this media. Try opening the original file, or read its text equivalent below.
Derived visual description
Explainer / 7:03
Compiled capability
The original audience explainer, with native playback, download and supplied source text.
We couldn’t load this media. Try opening the original file, or read its text equivalent below.
Supplied source text
Deep Dive / 22:00
How Vecco Med trains medical AI
An audio-only audience discussion, with native playback, original-file download and supplied source text.
How Vecco Med trains medical AI
Original source discussion. Play when you’re ready.
We couldn’t load this media. Try opening the original file, or read its text equivalent below.
Supplied source text
Slide Deck
Vecco Med strategic briefing
A PDF viewing copy of the supplied slide deck, with original PowerPoint and slide-reading text below.
PDF viewer unavailable on your device? Open the PDF directly or use the slide-by-slide text below.
We couldn’t load this media. Try opening the original file, or read its text equivalent below.
OCR-derived slide text
Also on Home: The Stepping-Stone Strategy 5:28 / video
Context & boundaries
Evidence & scope
Current stage
Vecco Med’s current direction is training-first encounter review and cumulative learning. Sources describe an earlier Vox(el).ai edge prototype tested with recorded EMS material and simulated patient data. Those tests do not establish training outcomes, live-field reliability, clinical accuracy or production readiness. This site does not establish deployed training capabilities, active pilots, customers, revenue or a proven learning advantage.
Human authority and information rights
Instructors retain responsibility for instruction, evaluation and curriculum. Qualified clinicians remain responsible for assessment, protocol use, diagnosis, treatment, handoff and final documentation. The system is information support, not autonomous educational or clinical authority. Capture, retention, access and reuse require appropriate purpose, permissions, governance and law; an encounter is not automatically company-owned data. Design principles do not establish privacy, security, compliance, universal offline operation or error-free outputs.
Evidence and future use
The next proposed step is a bounded training evaluation: defined workflow, baseline, measures, review burden, failure handling and decision gates. Field expansion is conditional on training value, governance, economic fit, approval and evidence of transfer—not a current offering or promised outcome. Original media contain source claims; supplied recording text is not verified word-for-word, and visual/OCR readings can contain errors. Attribution and public-use rights remain subject to review.
These are original project materials, not independently verified evidence. Product, clinical, performance, market, financial, and future-state assertions in the media remain source claims, not established facts or approved commitments.
Reveal AI Notes
Interpretation & evidence boundaries
Vox(el).ai is the prototype project name. Original source materials retain their original branding.
Vecco Med’s current direction is training-first encounter review and cumulative learning. Sources describe the earlier Vox(el).ai edge prototype tested with recorded EMS material and simulated patient data—not training or field validation. Bounded training evaluation is proposed next; field expansion remains conditional on training evidence, governance, economic fit, approval and demonstrated transfer.
Instructors retain responsibility for instruction, evaluation and curriculum. Information support, not autonomous care. Qualified clinicians remain responsible for assessment, protocol use, diagnosis, treatment, handoff, and final documentation.
These are original project materials, not independently verified evidence. Product, clinical, performance, market, financial, and future-state assertions in the media remain source claims, not established facts or approved commitments.
The intro photographs are prior AI-generated illustrations, not documentary evidence of a team, deployment, partner or product performance.
Local-first is a design direction, not proof of universal offline operation, privacy, security, compliance, reliability or integration. No customer, active pilot, clinical outcome, approved financing or contact service is represented here.
These same notes are available to every visitor. Evidence & scope · Plain-text guide · Canonical content JSON · No-JavaScript page index